
Rapid Review·Cardiovascular
Select any text to highlight it or add a note.
PATHOLOGY
T1Must knowConduction Blocks
P312
Videos
1 to play here
Play 1 here
Focus on
Four AV blocks, three benign to ominous and one requiring a pacemaker on sight.
Key takeaways
The four AV blocks
The split that matters
first-degree and Mobitz I are an AV node problem, mild and self-limited; Mobitz II and third-degree are a His-Purkinje problem, more severe, and need a pacemaker.First-degree AV block
PR interval above 200 msec, but every beat conducts, as on the first-degree block tracing. No treatment required, it is benign and asymptomatic.Second-degree, Mobitz type I (Wenckebach)
the PR interval lengthens progressively until a beat is dropped, i.e. a P wave with no QRS after it, as on the Wenckebach tracing. The RR intervals vary in a repeating pattern, so the rhythm is regularly irregular. No treatment required.Second-degree, Mobitz type II
dropped beats with a CONSTANT PR interval before them, as on the Mobitz II tracing. It usually reflects a structural abnormality such as ischemia or fibrosis, and may progress to third-degree block. Treatment is usually a pacemaker.Third-degree (complete) AV block
P waves and QRS complexes are rhythmically dissociated, as on the complete heart block tracing: the P waves march at the SA node's rate, the QRS complexes at the His bundle's escape rate, the RR intervals are regular, the atria and ventricles beat independently, and the atrial rate exceeds the ventricular rate. Causes: ischemia, infiltration (sarcoidosis), Lyme disease ("Lym3 disease"), and age-related fibrosis. Treatment is a pacemaker.| Block | ECG finding | Progresses? | Treatment |
|---|---|---|---|
| First-degree | PR above 200 msec, every beat conducts | No | None |
| Mobitz I (Wenckebach) | PR progressively lengthens, then a beat drops | Rarely | None |
| Mobitz II | Dropped beats with a constant PR | YES, to third-degree | Pacemaker |
| Third-degree (complete) | P waves and QRS fully dissociated, atrial rate faster | Already complete | Pacemaker |
| Feature | Mobitz I | Mobitz II |
|---|---|---|
| PR before the dropped beat | Progressively lengthens | Constant |
| Underlying cause | AV nodal, often functional | Structural: ischemia or fibrosis |
| Risk | Benign | Progresses to complete block |
| Treatment | None | Pacemaker |
Bundle branch block
What happens
conduction through one bundle is interrupted, so that ventricle depolarizes by slow myocyte-to-myocyte spread from the other, which depolarized through the fast His-Purkinje system. The left bundle version is on the left bundle branch block.Causes
commonly degenerative change, cardiomyopathy, or infiltrative disease.Premature beats
Premature atrial contraction
an extra beat from an ectopic atrial focus rather than the SA node. Narrow QRS with a preceding P wave, as on the PAC tracing. Often from increased adrenergic drive such as caffeine. Benign, though it raises the risk of AF and flutter.Premature ventricular contraction
an ectopic beat from the ventricle. Wide QRS with no preceding P wave, as on the PVC tracing. The shortened diastolic filling time lowers stroke volume for that beat. Prognosis depends largely on the underlying heart disease.| Feature | PAC | PVC |
|---|---|---|
| QRS | Narrow | Wide |
| Preceding P wave | Present | Absent |
| Origin | Atrial ectopic focus | Ventricle |
| Trigger | Increased adrenergic drive, caffeine | Varies |
| Significance | Benign, raises AF and flutter risk | Depends on the underlying heart disease |
Pacemakers
How they work
they mimic the intrinsic pacemaker in two ways. Activation (capture) sends an impulse that produces a ventricular contraction, seen on ECG as a pacing spike followed by a QRS. Sensing detects native beats so the device holds its fire when it is not needed, seen as an appropriate pause in spikes after a native QRS.Types
single-chamber (one lead, in the RA or RV), dual-chamber (one lead in the RA and one in the RV, to coordinate atria and ventricles), and biventricular (two or three leads: RA, RV, plus a third pacing the LV).Anatomy of the leads
the RA and RV leads travel through the left subclavian vein and SVC; the LV lead passes from the RA into the coronary sinus, which lies in the posterior atrioventricular groove. An RV lead can damage the tricuspid valve and cause tricuspid regurgitation.Two tracings both drop a QRS now and then. On one the PR interval stretches before the drop; on the other it never changes. Which patient gets the pacemaker?
The one with the constant PR: that is Mobitz II, a His-Purkinje lesion that can progress to complete block. The stretching PR is Wenckebach and needs nothing.
How it's tested
The whole point of this page is that Mobitz I needs nothing while Mobitz II needs a pacemaker, and the only way to tell them apart is whether the PR interval lengthens before the dropped beat. Practise reading that on the tracing rather than from the label. Third-degree block in a young person with a rash and joint pains is Lyme disease, and First Aid spells it Lym-three to fix which block it causes.
Go deeper
First Aid 2026 — CV/Pathology (p.312) · B&B — Heart blocks · Mehlman — HY Cardio (Wenckebach vs Mobitz II, Lyme carditis)
High-yield images7
Flashcards for this page
Card 1 of 5 · try-out only, nothing is saved
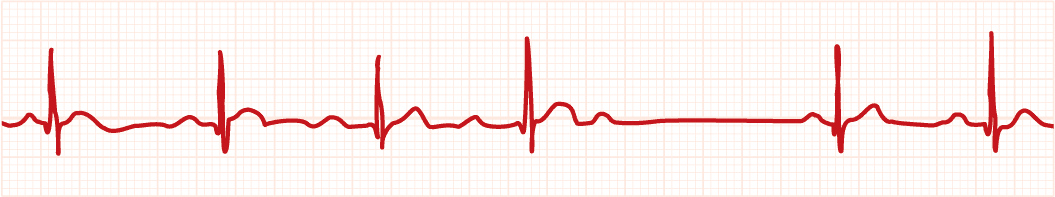
(...) atrioventricular block
You just read one page of 944
The rest of Step 1, written exactly like this.
Rapid Review is the reading layer of a full Step 1 platform: a schedule fitted to your exam date, flashcards for every page, and a mentor a message away.
Every Step 1 system
Written the same way: what to know, how it’s tested, where to go deeper.
A plan built to your exam date
Tell us when you sit, and the schedule fits the whole library and your question bank to it.
Flashcards for every page
Ready-made spaced-repetition decks linked to each topic, so nothing you read gets forgotten.
