
Rapid Review·General Pathology
Select any text to highlight it or add a note.
INFLAMMATION
T1Must knowAcute Inflammation
P209–P210
Focus on
The cardinal signs mapped to their exact mediators, and the five ways the response can end.
Key takeaways
Why inflammation exists
Why inflammation exists
to eliminate the cause of injury, clear necrotic cells, and initiate repair. It harms the host when excessive (septic shock), prolonged (TB), or inappropriate (SLE).Acute inflammation
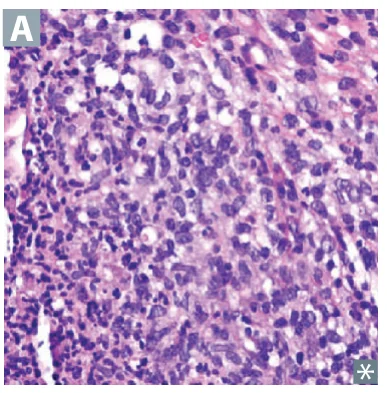
Acute inflammation
onset in seconds to minutes, lasting minutes to days. Dominant cell = neutrophil. This is an innate immune response.- Mediators: TLRs, arachidonic acid metabolites, neutrophils, eosinophils, pre-existing antibodies, mast cells, basophils, complement, Hageman factor (XII).
- Inflammasome: a cytoplasmic complex that recognizes DAMPs and PAMPs (microbial products, uric acid crystals) → IL-1 activation → fever and leukocytosis.
The cardinal signs
Cardinal signs and their mediators
- Rubor and calor (redness, warmth): vasodilation of arteriolar smooth muscle → ↑ blood flow. Mediated by histamine, prostaglandins, bradykinin, NO.
- Tumor (swelling): endothelial cell contraction → ↑ vascular permeability → protein-rich exudate leaks from postcapillary venules → ↑ interstitial oncotic pressure. Mediated by leukotrienes C4/D4/E4, histamine, serotonin, bradykinin.
- Dolor (pain): sensitization of sensory nerve endings by bradykinin, PGE2, histamine.
- Functio laesa (loss of function).
Fever and the macrophage cytokines
Fever mechanism
pyrogens (LPS) → macrophages release IL-1 and TNF → ↑ COX activity in perivascular cells of the anterior hypothalamus → ↑ PGE2 → the temperature set point rises.The macrophage cytokine trio, each with its own job
IL-1 causes fever, TNF-α causes vasodilation and vascular permeability (and therefore hypotension), IL-6 drives hepatic acute-phase protein release, and IL-12 pushes CD4+ T cells toward Th1.Septic shock
Two routes to septic shock, both ending in massive cytokine release
- Endotoxin: lipid A of LPS binds CD14/TLR4 on macrophages → TNF-α and IL-1 flood out.
- Superantigen: TSST-1 of S. aureus or exotoxin A of S. pyogenes bridges MHC-II on the macrophage directly to the T-cell receptor, bypassing antigen specificity and activating a huge fraction of T cells at once.
How the response unfolds and ends
The two components of the acute response
- Vascular: vasodilation and ↑ endothelial permeability.
- Cellular: extravasation of leukocytes (mainly neutrophils) from postcapillary venules → accumulation at the focus of injury → leukocyte activation. Extravasation itself has 4 steps: margination and rolling, tight adhesion, transmigration, and chemotaxis.
Five possible outcomes of acute inflammation
- Resolution and healing (IL-10, TGF-β).
- Persistent acute inflammation (IL-8).
- Abscess: acute inflammation walled off by fibrosis.
- Chronic inflammation: macrophage antigen presentation → CD4+ Th activation.
- Scarring.
Why do NSAIDs bring a fever down?
Pyrogens make macrophages release IL-1 and TNF, which raise COX activity in the anterior hypothalamus and so raise PGE2, the signal that resets the temperature set point. NSAIDs inhibit COX, so less PGE2 is made and the set point falls.
How it's tested
The fever question is mechanistic, not clinical: LPS → macrophage IL-1 and TNF → ↑ COX activity in the perivascular cells of the anterior hypothalamus → ↑ PGE2 → the set point rises. The set point moving is the answer, not heat production.
The other recurring stem is septic shock by superantigen. TSST-1 of S. aureus and exotoxin A of S. pyogenes bridge MHC-II directly to the T-cell receptor, bypassing antigen specificity, which is what separates them from the endotoxin route through CD14/TLR4.
Go deeper
First Aid "Inflammation"; Pathoma Ch. 2 "Inflammation"; Boards & Beyond. Anchor the cardinal signs mapped to their mediators, the macrophage cytokine trio (IL-1 fever, TNF-α permeability, IL-6 acute-phase proteins), and the five outcomes of an acute episode.
High-yield images1
Flashcards for this page
Card 1 of 5 · try-out only, nothing is saved
A protein complex that recognizes (...) products, (...), and products of (...) cells to induce inflammation
You just read one page of 944
The rest of Step 1, written exactly like this.
Rapid Review is the reading layer of a full Step 1 platform: a schedule fitted to your exam date, flashcards for every page, and a mentor a message away.
Every Step 1 system
Written the same way: what to know, how it’s tested, where to go deeper.
A plan built to your exam date
Tell us when you sit, and the schedule fits the whole library and your question bank to it.
Flashcards for every page
Ready-made spaced-repetition decks linked to each topic, so nothing you read gets forgotten.
