
Rapid Review·Cardiovascular
Select any text to highlight it or add a note.
Valvular Heart Disease
T1Must knowMitral Regurgitation
Focus on
A blowing holosystolic apical murmur to the axilla, louder with handgrip and leg raise. Primary MR (prolapse, endocarditis, rheumatic, ruptured chordae) gets valve repair when symptomatic or when the EF slips to 60%; secondary MR gets heart-failure therapy first. Acute MR after an MI or endocarditis is pulmonary edema with a soft murmur and an emergency operation.
Key takeaways
Causes
Primary (the valve itself)
mitral valve prolapse (the most common cause in developed countries), infective endocarditis, rheumatic disease.Secondary
two types.- Functional regurgitation from a dilated failing ventricle.
- Ischemic regurgitation from papillary muscle or chordal rupture after a myocardial infarction.
Clinical features
Acute regurgitation
an abrupt rise in left atrial and ventricular filling pressures causes acute heart failure and pulmonary edema, sometimes cardiogenic shock.Chronic regurgitation
from asymptomatic to left heart failure (dyspnea, fatigue, an S3 gallop).Palpitations
atrial fibrillation is common once the left atrium enlarges.
What this shows
The murmur
a holosystolic blowing murmur at the apex radiating to the axilla.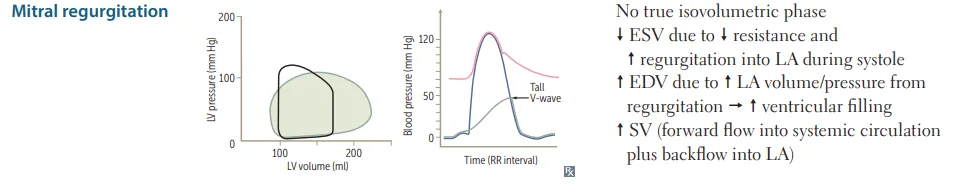
What this shows
Louder with more preload (leg raise) or more afterload (handgrip)
because more blood regurgitates.Diagnosis
Transthoracic echocardiography in chronic disease
left atrial and ventricular dilation, with a falling ejection fraction once decompensated.In acute regurgitation
the chambers are still normal in size and the ejection fraction is normal or high.Management
Acute regurgitation
emergency valve repair or replacement.Chronic primary regurgitation
surgery when symptomatic, or asymptomatic with an ejection fraction under 60 percent.Secondary regurgitation
medical therapy for the heart failure (Heart Failure).| Acute | Chronic | |
|---|---|---|
| Presentation | Acute heart failure, pulmonary edema, sometimes shock | Asymptomatic to left heart failure, atrial fibrillation |
| Chambers on echo | Normal size | Left atrium and ventricle dilated |
| Ejection fraction | Normal or high | Falls once decompensated |
| Treatment | Emergency repair or replacement | Surgery if symptomatic or ejection fraction under 60 percent (primary); heart failure therapy (secondary) |
Four days after an inferior myocardial infarction, a patient suddenly develops pulmonary edema and hypotension with a new apical systolic murmur; echo shows normal-sized chambers and a high ejection fraction. What is the likely cause and the treatment?
Acute ischemic mitral regurgitation from papillary muscle rupture: the chambers have not had time to dilate, and the ejection fraction is normal or high. It needs emergency valve repair or replacement.
How it's tested
Asymptomatic woman with MVP, a holosystolic apical murmur to the axilla, severe MR on echo and an EF of 58%: mitral valve repair — an EF of 60% is already dysfunction in MR.
Day 4 after an inferior MI: sudden pulmonary edema, hypotension and a soft apical murmur: posteromedial papillary muscle rupture — echo, balloon pump, emergency surgery.
HFrEF with a dilated LV, tethered leaflets and moderate MR: secondary MR — optimize GDMT and CRT before any valve intervention.
Which maneuver makes the MR murmur louder: handgrip (more afterload) and leg raise (more preload); Valsalva softens it.
Severe primary MR in a patient at prohibitive surgical risk: transcatheter edge-to-edge repair.
Go deeper
Guidelines: 2020 ACC/AHA Valvular Heart Disease Guideline
Related Step 2 pages: Mitral Valve Prolapse, Mitral Stenosis, Post MI Complications, Infective Endocarditis, Heart Failure, Heart Sounds & Murmurs
High-yield images2
Flashcards for this page
Card 1 of 5 · try-out only, nothing is saved
You just read one page of 236
The rest of Step 2 CK, written exactly like this.
Rapid Review is the reading layer of a full Step 1 platform: a schedule fitted to your exam date, flashcards for every page, and a mentor a message away.
Every Step 1 system
Written the same way: what to know, how it’s tested, where to go deeper.
A plan built to your exam date
Tell us when you sit, and the schedule fits the whole library and your question bank to it.
Flashcards for every page
Ready-made spaced-repetition decks linked to each topic, so nothing you read gets forgotten.
